









Are Compression Garments Good for Varicose Veins?
What the clinical evidence says and how to use compression therapy effectively
Yes - compression garments are genuinely good for varicose veins. Graduated compression stockings are considered a first-line treatment by vascular specialists worldwide, clinically proven to reduce the aching, swelling, and heaviness varicose veins cause. They do not make existing veins disappear, but they meaningfully improve quality of life and can slow disease progression.
Why Varicose Veins Are More Than a Cosmetic Problem
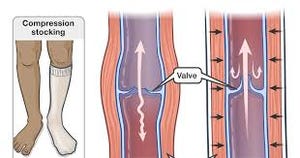
Varicose veins affect roughly 23% of adults worldwide, with higher rates among people who stand for long hours, those who are pregnant, and those with a family history of venous disease. They occur when the one-way valves inside the leg veins fail. Blood that should travel upward toward the heart pools instead, stretching vein walls and creating the visible, twisted bulges under the skin.
This pooling - called chronic venous insufficiency (CVI) when persistent - produces a cascade of symptoms: dull aching, night cramps, skin itching around the vein, and swelling that worsens through the day. Left untreated, severe CVI can progress to skin changes, venous eczema, and leg ulcers. That is why conservative management with compression therapy matters and why it is recommended early in the disease course.
How Compression Garments Actually Work
Compression stockings apply graduated pressure - highest at the ankle, tapering as they move up the leg. This gradient is intentional and clinically important. It mimics and enhances the pumping action that leg muscles provide during walking, pushing venous blood upward through the deep venous system toward the heart.
Without adequate support - during long periods of standing, sitting, or in people with damaged valves - blood pools in the lower legs. This pooling raises pressure inside the surface veins, causing them to stretch and bulge further. Compression garments reduce this distension, which improves the efficiency of whatever valve function remains and slows the progressive enlargement of the veins.
Graduated vs. Uniform Compression
This distinction matters enormously. Graduated compression - where pressure is strongest at the ankle and decreases toward the knee or thigh - is what clinical guidelines recommend. Uniform support hosiery applies the same pressure throughout and is substantially less effective at improving venous return. When selecting compression socks or stockings for varicose veins, always confirm the label says graduated compression.
Choosing the Right Compression Level
Compression pressure is measured in millimeters of mercury (mmHg). The level you need depends on the severity of your venous disease. Most over-the-counter compression socks fall in the 15 to 20 mmHg range, which is adequate for mild symptoms or prevention. Clinical grades require a prescription and professional fitting.
| Compression Level | Pressure | Best For | Rx Required? |
|---|---|---|---|
| Mild / Preventive | 8-15 mmHg | Travel fatigue, minor aching, low-risk prevention | No |
| Moderate | 15-20 mmHg | Mild varicose veins, pregnancy with doctor guidance, long-haul flights | No |
| Firm (Medical Grade I) | 20-30 mmHg | Moderate varicose veins, mild edema, post-sclerotherapy recovery | Often recommended |
| Extra Firm (Medical Grade II) | 30-40 mmHg | Severe CVI, venous ulcers, post-surgical recovery | Yes |
| Highest (Prescription Only) | 40-50 mmHg | Severe lymphedema, post-thrombotic syndrome - always fitted by a clinician | Yes |
For most people with symptomatic but uncomplicated varicose veins, the 20 to 30 mmHg range is the clinical sweet spot - effective enough to produce noticeable improvement without requiring prescription-level fitting.
What the Research Actually Shows
The clinical literature on compression therapy for varicose veins and chronic venous insufficiency is among the more robust bodies of evidence in conservative vascular medicine.
Symptom Relief Is Well Supported
A landmark study published in Phlebology found that patients wearing 20 to 30 mmHg graduated compression stockings reported significant reductions in leg pain, heaviness, and swelling compared to controls. This finding has been replicated across multiple populations and study designs. The overall evidence is sufficient that compression therapy appears in the first-line recommendations of guidelines from the American Venous Forum, the Society for Vascular Surgery, and European vascular bodies.
Slowing Disease Progression
Beyond symptom management, consistent compression use appears to slow the worsening of venous insufficiency. A prospective study in the Journal of Vascular Surgery found that CVI patients who wore compression regularly showed significantly less deterioration of skin and subcutaneous tissue over a three-year follow-up period compared to those who did not. This suggests compression is not merely masking symptoms - it is modifying the disease course by reducing the chronic venous hypertension that drives tissue damage.
Post-Procedure Recovery
After minimally invasive procedures like endovenous laser ablation (EVLA), radiofrequency ablation, or sclerotherapy, vascular surgeons routinely prescribe compression to support vein closure, reduce post-procedural bruising, and limit the risk of deep vein thrombosis. Clinical protocols at leading vascular centers typically recommend 2 to 6 weeks of consistent compression following such procedures.
What Compression Garments Cannot Do
Setting accurate expectations is important. Compression stockings are excellent for symptom management, but they are not a cure. They will not:
- Make existing varicose veins shrink or disappear permanently
- Repair damaged or incompetent venous valves
- Eliminate the underlying venous reflux driving the disease
- Replace medical evaluation or anticoagulation for active venous thrombosis
- Substitute for procedures such as sclerotherapy, laser ablation, or phlebectomy in people seeking to eliminate veins entirely
Think of them the way you would think of glasses: they correct the functional problem while worn, but do not fix the underlying anatomy. For elimination of varicose veins rather than symptom management, procedures remain necessary.
Practical Takeaways: How to Use Compression Therapy Effectively
Knowing that compression works is one thing. Wearing it correctly and consistently is what produces actual benefit. Here is how to make it work:
- Put them on first thing in the morning before swelling develops, ideally before getting out of bed when venous pressure is at its lowest
- Get properly measured - measure ankle circumference, calf circumference, and leg length for sizing; a poorly fitting stocking is ineffective or harmful if it rolls or bunches
- Choose graduated compression and not uniform compression - verify the label; athletic compression socks and travel socks are not all clinically equivalent
- Wear them consistently throughout the day and remove at night unless instructed otherwise by your doctor; sporadic use produces minimal benefit
- Replace every 3 to 6 months - elasticity degrades with washing and wear, reducing therapeutic pressure below effective levels
- Pair with movement and elevation - compression works best alongside regular walking, calf-raise exercises, and leg elevation during rest
- Follow your doctor's protocol after procedures - post-sclerotherapy and post-ablation compression requirements vary; follow the prescribed duration precisely
Frequently Asked Questions
The Bottom Line
Compression garments are genuinely good for varicose veins - not as a marketing promise, but as a clinically validated therapeutic intervention. For the majority of people with symptomatic varicose veins or chronic venous insufficiency, graduated compression stockings in the 20 to 30 mmHg range offer meaningful, evidence-backed relief from pain, swelling, and leg fatigue.
They are not a cure, and they will not erase existing veins. But worn correctly and consistently, they are one of the safest, most accessible, and most cost-effective tools available for managing venous disease - whether treating mild symptoms conservatively or recovering from a vascular procedure.
If you have not yet spoken with a vascular specialist or phlebologist about your symptoms, that is the natural next step. A venous duplex ultrasound can map the extent of valve dysfunction and guide both compression choices and any procedural decisions.